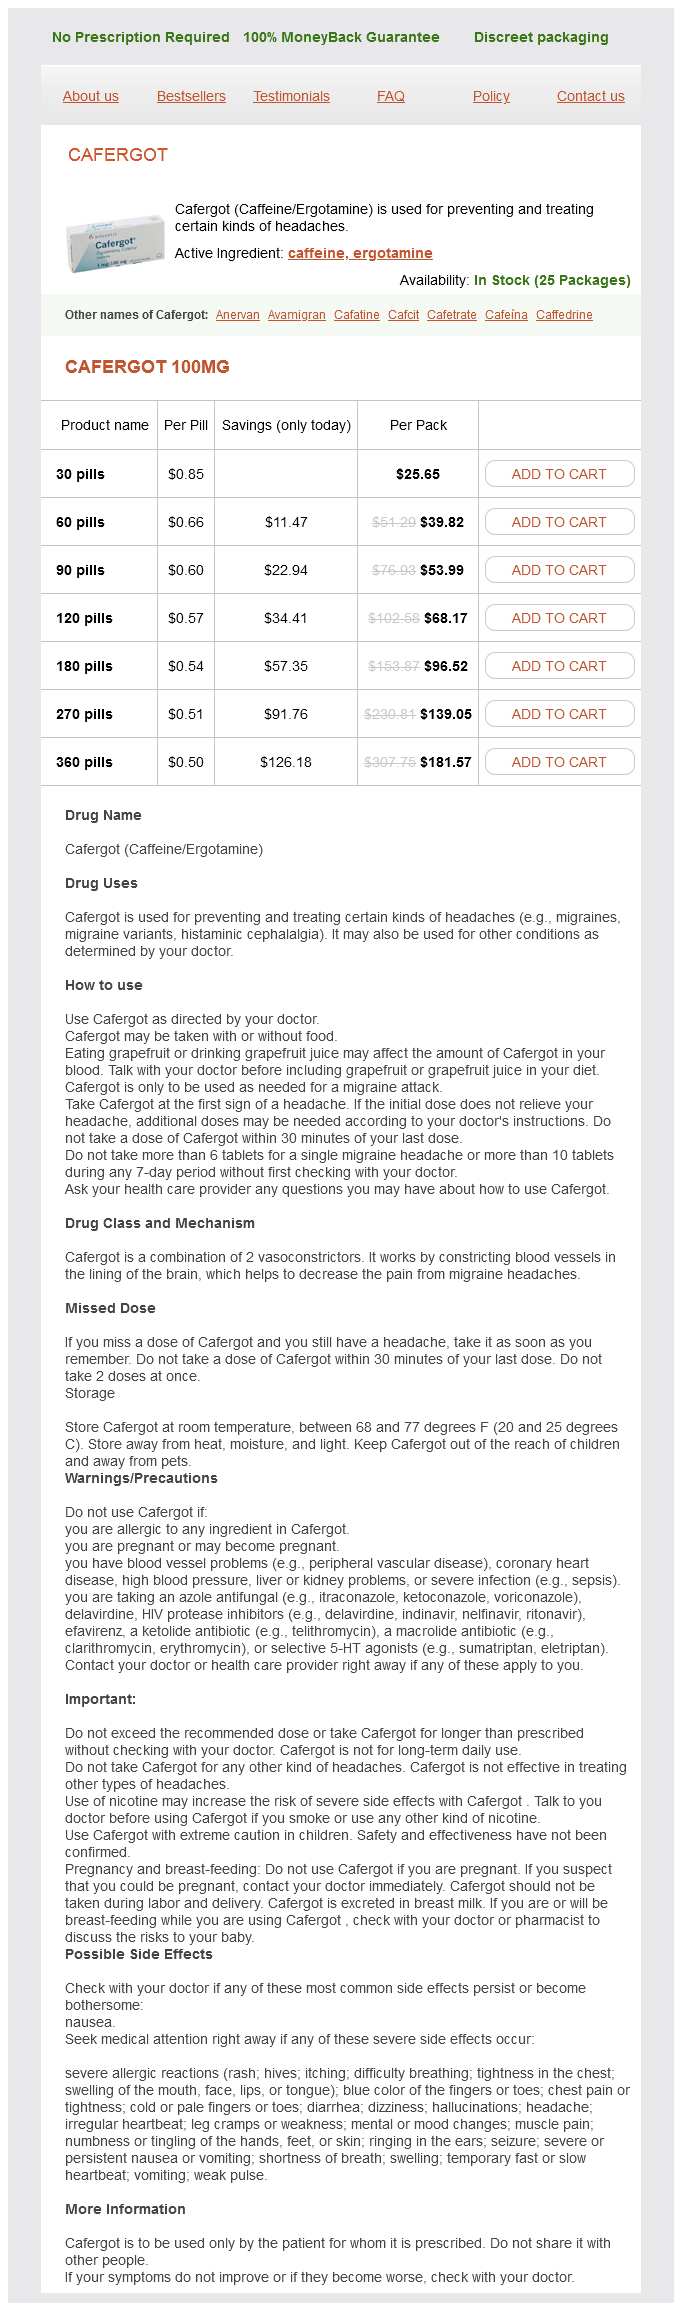
Cafergot 100mg
Cafergot dosages: 100 mg
Cafergot packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 637
Only $0.54 per item
Increased pigmentation pain treatment hypnosis generic cafergot 100 mg buy, especially skin creases, recent scars, and inside cheeks Fatigue, weakness Depression Nausea and weight loss Postural hypotension Salt craving Abdominal pain, vomiting, diarrhea Confusion leading to coma Amenorrhea, decreased libido Loss of axillary and pubic hair in postmenopausal women Associated autoimmune disorders: vitiligo, alopecia, thyroid disease, type 1 diabetes mellitus (25%50% of patients) Table 13. Primary adrenal failure is frequently accompanied by a darkening of the skin and such an occurrence should arouse suspicion (Table 13. Recognizing its presence, especially in the setting of acutely stressful events. Our approach in the emergency room is to treat with exogenous corticosteroids immediately, before confirmatory laboratory testing and then document steroid deficiency later. Typical physical signs and symptomatology include nausea and vomiting, hypoglycemia, hypotension (especially that proving to be refractory to treatment), abdominal pain, and mental confusion lapsing into frank coma. Clues to the diagnosis are the presence of hyponatremia; hyperkalemia; raised urea and creatinine; hypoglycemia; hypercalcemia; a normochromic; normocytic anemia; eosinophilia; and neutropenia. Definitive diagnosis depends on demonstrating a low cortisol, excluding secondary adrenal failure due to pituitary disease and determining the etiology. Blood should be stored for retrospective analysis and the treatment commenced immediately in this setting. Antibody-positive individuals with normal cortisol levels are at risk of developing adrenal failure and must be followed up. Treatment consists of an intravenous or intramuscular injection of 100 mg of hydrocortisone, followed by an intravenous infusion of 4 mg/h or 6 hourly intramuscular injections of 50100 mg. Patients are usually severely dehydrated and require rapid fluid replacement with normal saline. Electrolytes need to be closely monitored because the potassium levels usually fall rapidly and require supplementation in the saline infusion. Fluid replacement needs to be closely monitored by urine output and blood pressure. Particular care needs to be taken with elderly patients and patients with underlying cardiac disease. The usual replacement dose of hydrocortisone 2030 mg/day is given in divided doses, with the highest dose taken in the morning immediately on waking. At minimum, there should be a second dose early evening, but many patients benefit from a third dose at lunchtime. Anticonvulsant drugs and rifampicin increase hydrocortisone clearance, and patients taking these medications may require higher doses of replacement therapy. In addition, fludrocortisone is required to provide mineralocorticoid replacement. The dose is adjusted to ensure a normal blood pressure with the absence of edema, together with measurement of electrolytes and plasma renin, which should be in the upper half of the reference range. Diarrhea and vomiting in particular are associated with the risk of adrenal crisis.
Oxitriptan (5-Htp). Cafergot.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96772
Nephrology pain medication for dogs surgery 100 mg cafergot buy with amex, Dialysis, Transplantation: Official Publication of the European Dialysis and Transplant Association European Renal Association 2008; 23(5): 15628. Nephrology, Dialysis, Transplantation: Official Publication of the European Dialysis and Transplant Association European Renal Association 2006; 21(6): 15649. Current prescriptions for the correction of hyponatraemia and hypernatraemia: Are they too simple Nephrology, Dialysis, Transplantation: Official Publication of the European Dialysis and Transplant Association European Renal Association 2002; 17(7): 117680. Nephrology, Dialysis, Transplantation: Official Publication of the European Dialysis and Transplant Association European Renal Association 2008; 23(11): 35018. Nephrology, Dialysis, Transplantation: Official Publication of the European Dialysis and Transplant Association European Renal Association 2007; 22(12): 34717. Gender and age as risk factors for hypokalemia and hyperkalemia in a multiethnic Asian population. Clinica Chimica Acta; international Journal of Clinical Chemistry 2003; 331(12): 1712. Inherited primary renal tubular hypokalemic alkalosis: A review of Gitelman and Bartter syndromes. Sweat rate and fluid turnover in American football players compared with runners in a hot and humid environment. New guidelines for potassium replacement in clinical practice: A contemporary review by the National Council on Potassium in Clinical Practice. Hyperkalemia in hospitalized patients: Causes, adequacy of treatment, and results of an attempt to improve physician compliance with published therapy guidelines. Trimethoprim-induced hyperkalaemia: Clinical data, mechanism, prevention and management. Drug safety: An international Journal of Medical Toxicology and Drug Experience 2000; 22(3): 22736. The transtubular potassium concentration in patients with hypokalemia and hyperkalemia. American Journal of Kidney Diseases: the Official Journal of the National Kidney Foundation 1990; 15(4): 30915. Nephrology, Dialysis, Transplantation: Official Publication of the European Dialysis and Transplant Association European Renal Association 1989; 4(3): 22832. Nephrology, Dialysis, Transplantation: Official Publication of the European Dialysis and Transplant Association European Renal Association 2003; 18(11): 221518. Connell, Marie Freel Introduction Hypertension is well recognized as an important risk factor for the development of cardiovascular disease. This relationship has been further highlighted by a recent meta-analysis demonstrating that hypertension accounts for more than 7 million excess deaths per year worldwide. A significant number of endocrine conditions, including acromegaly, primary hyperparathyroidism, and hyperthyroidism, are associated with hypertension, but the underlying mechanisms in these circumstances are unclear. In contrast, there are several examples of endocrine disease in which hypertension features prominently as a direct result of hormonal abnormalities.
The subdivisions of the adenohypophysis are the pars distalis or anterior lobe pain treatment in dvt discount cafergot 100 mg with mastercard, the pars intermedia or intermediate lobe, and the pars tuberalis, which encircles the neural stalk. The subdivisions of the neurohypophysis are the posterior lobe, also called the neural lobe or infundibular process, the neural stalk, which connects the hypothalamus with the posterior lobe, and the median eminence, a midline eminence on the ventral surface of the hypothalamus, which is the portion of the neural stalk that ascends from the hypothalamus. The neural stalk and the pars tuberalis of the adenohypophysis form the pituitary stalk. The anterior lobe and posterior lobe are clearly separated and can easily be distinguished with the naked eye. It is composed of three parts: an olive-shaped swelling, called the tuberculum sellae, which is located anteriorly; a seatlike depression, called the hypophysial fossa, for the pituitary gland; and the posterior part of the saddle, known as the dorsum sellae. There is a central opening on the sellar diaphragm through which the hypophysial stalk passes through in connecting the hypothalamus to the pituitary. The optic chiasma lies directly above the sellar diaphragm ahead of the hypophysial stalk. Space-occupying lesions in the pituitary may compress and compromise the tuber cinereum and cause hypothalamo-hypophysial dysfunctions. The lateral walls of the sella are close to the cavernous sinuses containing the internal carotid arteries and several nerves including the oculomotor, trochlear, and abducens nerves and the first two branches of the trigeminal nerve. The sphenoid sinus, separated from the sella by a thin layer of bone, is inferior to the pituitary. In the case of a pituitary tumor, this bone may be resorbed and eroded, leading to tumor penetration into the sinus. Blood Supply the blood supply of the pituitary derives from two groups of arteries: from above, the right and left superior hypophysial arteries; from below, the right and left inferior hypophysial arteries. The superior hypophysial arteries supply blood to the median eminence and proximal portion of the pituitary stalk. The capillaries of this plexus rejoin to form the long portal vessels that traverse the pituitary stalk and break up into a secondary capillary plexus in the anterior lobe of the pituitary in close relationship to the cells of anterior pituitary. This hypophysial portal vascular system is of the utmost importance in regulating hormone secretion of the anterior pituitary. The posterior pituitary receives its blood supply from the inferior hypophysial arteries. Some vessels from the posterior lobe penetrate into the anterior pituitary (short portal vessels). Venous blood leaves the pituitary through dural channels and enters the cavernous sinuses, which drain to the inferior petrosal sinus and the internal jugular vein. There may be anastomoses between the petrosal sinuses, which can lead to confusing observations with petrosal sinus sampling. Although most blood flow is from the hypothalamus to the pituitary, there is evidence that some blood may flow in the opposite direction, from the anterior pituitary to the hypothalamus. These nerve fibers are not believed to have major importance in the control of hormone secretion. The posterior pituitary contains the axon terminals of 92 Pituitary Gland Anatomy and Embryology the supraoptic and paraventricular neurons, synthesizing and releasing oxytocin and vasopressin.
Syndromes
Additional information:
Usage: q.2h.
Tags: cheap 100 mg cafergot amex, cheap cafergot 100 mg buy online, cafergot 100 mg purchase amex, 100 mg cafergot amex
Osko, 28 years: The penile urethra runs through the corpus spongiosum (and is also called the spongy urethra). Pathogens responsible for these infections are bacteria (including mycobacterius tuberculosis), viruses, parasites and fungi. Peripheral ghrelin transmits orexigenic signals through the noradrenergic pathway from the hindbrain to the hypothalamus.
Irhabar, 30 years: Nicotinic receptors lead to depolarization of the chromaffin cell membrane followed by opening of voltage sensitive Ca2+ channels. Estradiol levels modulate brain activity and negative responses to psychosocial stress across the menstrual cycle. Induction of ovulation with low-dose gonadotropins in polycystic ovary syndrome: An analysis of 109 pregnancies in 225 women.
Sancho, 65 years: This may be imperative in the first trimester, when hyperemesis classically occurs, potentially leading to missed oral doses of corticosteroid. Sweat rate and fluid turnover in American football players compared with runners in a hot and humid environment. The primary action of calcitonin is a direct effect on osteoclasts to inhibit bone resorption.
Malir, 40 years: Management of endocrine disease: clinicopathological classification and molecular markers of pituitary tumours for personalized therapeutic strategies. Because the integrity of bone is absolutely dependent on Ca2+ and Pi, chronic dysregulation of Ca2+ and Pi levels, or of the hormones that regulate Ca2+ and Pi, leads to pathologic changes in bone. Levels do not show significant diurnal variation and so tests other than basal measurements are very rarely required.


